Off-the-shelf and bedside HSC engineering.
Banked engineered allogeneic HSCs — plus a bedside autologous path — for scalable, affordable treatment of genetic and immune disorders.
Engineering stem cells into off-the-shelf medicines.
Banked engineered allogeneic HSPCs for genetic and immune disorders, complemented by an autologous path for tolerance and a bedside manufacturing platform.
Hemavive engineers healthy-donor hematopoietic stem and progenitor cells with a single editing toolbox, tuned per program — so cells can be banked, cryopreserved and infused without HLA matching or donor-search delay.
Curative gene therapy already works. Almost nobody can get it.
Personalized manufacturing and busulfan conditioning keep curative therapy out of reach for almost everyone who needs it.
Three pillars on one HSC engineering foundation.
Banked donor products for diseases that need cells now, an autologous path for diseases that need tolerance, and a manufacturing concept that could bring both to the bedside.
Radiation injury, hemoglobinopathies and immune deficiencies — engineered to stay invisible to recipient immunity for as long as each disease requires.
A patient's own HSCs engineered to teach their immune system what to tolerate — in transplantation and in autoimmune disease.
A closed, automated engineering concept designed to bring controlled cell engineering to the point of care.
Engineered to be invisible to the recipient immune system.
Each program is defined by two independent design choices: how the cells achieve immune invisibility, and how long the graft is meant to persist. The same editing toolbox serves all three.
A stockpiled, off-the-shelf hematopoietic bridge for radiation-induced marrow failure. Active collaboration with HJF / AFRRI.
A banked, one-time infusion designed for durable, transfusion-independent correction — without a donor search.
A banked allogeneic HSPC product for rapid immune reconstitution, with HLA class I restored as the cells mature.
The cassette goes where we choose it to go.
Homology-directed repair places the cassette at a defined locus with known copy number and endogenous regulation left intact. Approved lentiviral products integrate semi-randomly — variable copy number and expression, and an insertional-mutagenesis risk to monitor for years.
Splitting the nuclease and the repair template across two vectors breaks the single-vector packaging limit.
Read the platform page →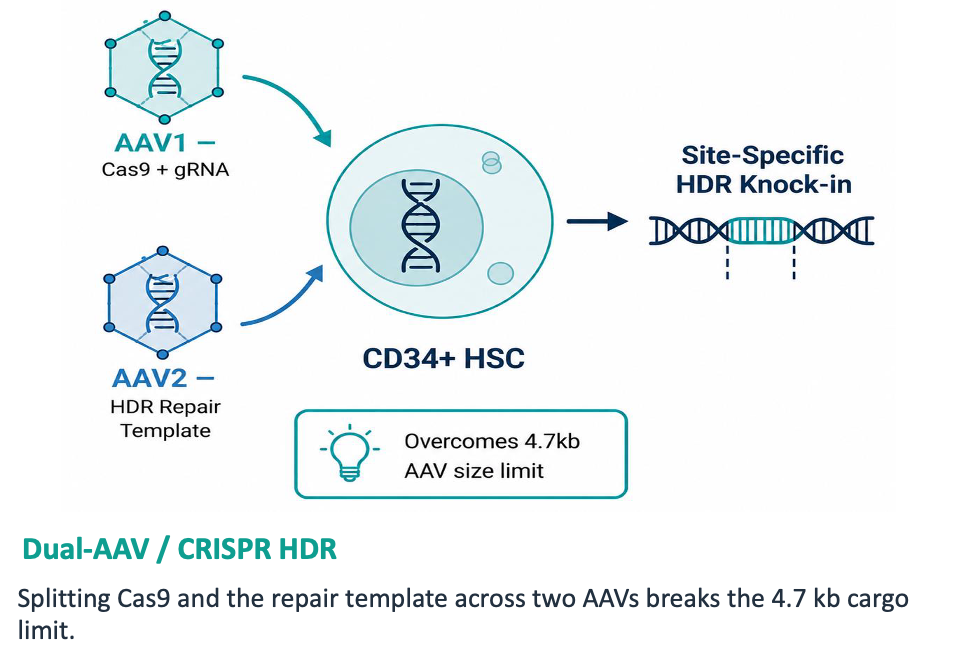
A closed, automated path to point-of-care manufacturing.
Hemavive is developing a closed-loop extracorporeal engineering concept designed to bring controlled cell engineering closer to the patient — reducing manufacturing complexity, improving standardization, and supporting scalable therapeutic workflows.
About ECEPTargets, not results. ECEP is in development, not yet clinically validated, and not required for the lead program's first IND-enabling path.
The same platform, turned toward tolerance.
Two directions apply HSC engineering to the patient's own cells, through two distinct mechanisms. Both are platform directions, not active clinical programs today.
Molecular mixed chimerism — a recipient's own HSCs engineered to present defined donor identity, so their immune system is educated to accept the graft. The graft itself is left biologically untouched.
Read more →Lineage-directed immunoregulatory programs designed to act only where inflammation is — off in the stem cell, off in healthy tissue, on in the inflamed gut or CNS.
Read more →Building a regional development and manufacturing presence in the Middle East.
Sickle cell disease and β-thalassemia are highly prevalent across the region. Hemavive is developing regional collaborations for co-development, local manufacturing and access.
Partner with Hemavive.
Hemavive is engaging with strategic investors, grant partners, engineering partners, and scientific collaborators to advance platform proof-of-concept studies.
Detailed technical materials are available under CDA / NDA.