One banked product, several SCID genotypes.
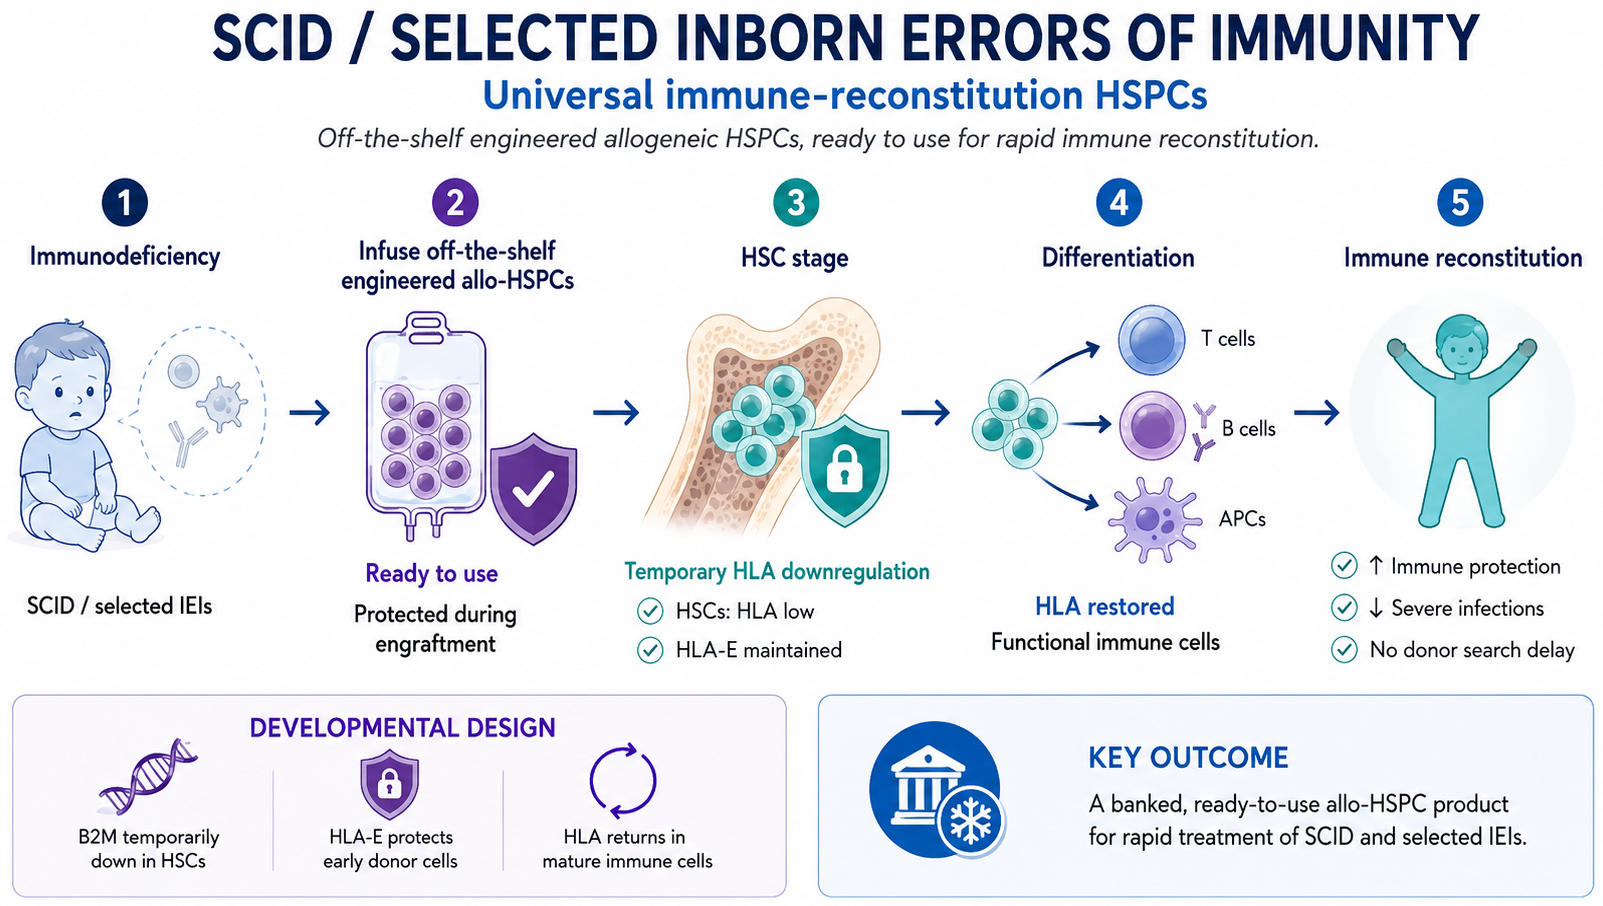
Transplant is curative in SCID when access is timely — but a donor search costs weeks, and gene therapy reaches only selected genotypes at selected centers. A banked donor product is genotype-agnostic and available on demand.
Timing decides the outcome.
SCID is a pediatric emergency. Outcomes depend heavily on how quickly a child reaches transplant, and only a minority of countries screen newborns for it today.
A product that is already banked, engineered and released removes the donor search from the critical path.
Invisible while engrafting, normal once mature.
Developmental invisibility protects the graft through engraftment, then hands back a fully functional immune system: HLA class I is restored as the cells mature, so the reconstituted immune compartment behaves normally.
A rare-disease cell & gene therapy route.
Cell & gene therapy IND path, developed for rare-disease and pediatric transplant settings.
CD34+ HSPC validation · multilineage immune reconstitution · genome-editing and insertion safety.
Children's National Hospital advisory relationship, into the U.S. pediatric transplant network.
Regulatory routes shown are planning hypotheses, not approval claims. Children's National is an advisory relationship, not a signed partnership.